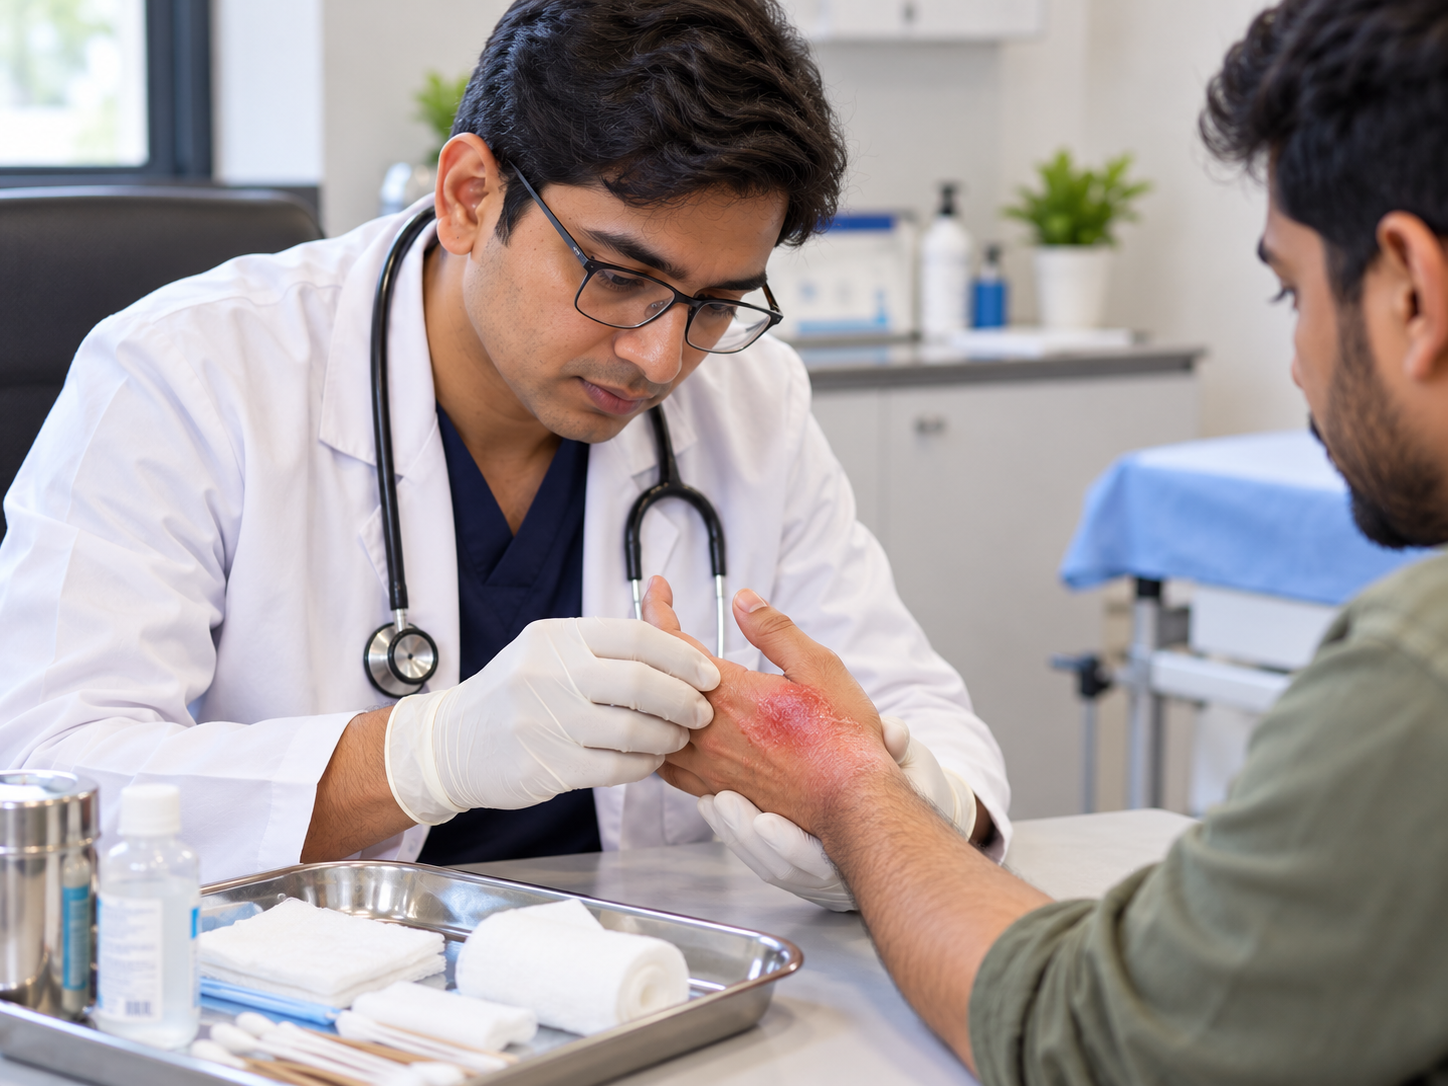
A burn management course for doctors should prepare GPs and casualty doctors to assess burn depth, estimate total body surface area (TBSA), provide 20 minutes of cool running water, select suitable wound dressings and recognise when urgent referral is necessary. During Diwali, these skills are particularly important because firecracker injuries can involve the hands, face and eyes, sometimes requiring specialist treatment.
Diwali celebrations increase the risk of burns caused by firecrackers, flames, hot objects and accidental clothing fires. Many patients initially visit a general practitioner or nearby casualty department rather than a specialist burn centre.
The first consultation can influence healing, infection risk, pain control and long-term scarring.
A GP should be able to distinguish a minor superficial burn from a potentially serious injury that requires specialist care.
At Elegance Vidhyalay, structured surgical education emphasises the importance of wound assessment, appropriate dressing techniques and recognising the limits of primary care.
This guide explains the essential burn management skills every doctor should develop before the festive season.
Firecrackers can cause several types of injuries, including thermal burns, blast injuries, eye injuries and penetrating wounds.
Common presentations include:
Some injuries appear minor initially but may involve deeper tissues.
For example, a small firecracker injury on a finger may involve significant tissue damage or associated blast trauma.
Doctors should therefore assess the mechanism of injury rather than relying only on the visible wound size.
Burn wounds can evolve during the first 24–72 hours.
An injury that initially appears superficial may later show signs of deeper tissue damage.
Early clinical assessment helps doctors:
A burn management course for doctors should include realistic emergency scenarios and practical decision-making exercises.
Initial burn management should follow a structured approach.
In major burns or blast injuries, evaluate the patient’s overall condition before focusing on the skin.
Look for:
Patients with suspected inhalation injury, airway compromise or major trauma require emergency transfer.
One of the most important first-aid principles is cooling the burn under cool running water for 20 minutes.
Cooling is most effective when started immediately and may still be beneficial if begun within approximately three hours of injury.
Use cool running tap water, not ice.
Do not apply:
These substances may worsen tissue damage, contaminate the wound or interfere with assessment.
Remove rings, watches and tight jewellery before swelling develops, provided they are not stuck to the skin.
Do not forcibly remove clothing or material adhering to the wound.
Cool the burn, not the entire patient.
Keep the rest of the body warm, particularly in children and patients with extensive burns.
After cooling, protect the burn with a clean, non-adherent covering.
For initial transfer, a clean dressing or suitable plastic film laid loosely over the burn may be used. Do not wrap film circumferentially around a limb.
Accurate burn assessment is an essential component of burn depth assessment training.
Doctors should evaluate both the depth and the percentage of body surface area involved.
Burns are commonly classified into four broad categories.
Superficial Burns
These affect the epidermis.
Typical features include redness, pain and dry skin without blistering.
They usually heal without significant scarring.
Superficial Partial-Thickness Burns
These involve the epidermis and superficial dermis.
The wound may appear pink, moist and blistered.
Pain is often significant.
With appropriate care, uncomplicated injuries may heal within approximately two weeks.
Deep Partial-Thickness Burns
These extend deeper into the dermis.
The wound may appear pale, mottled or less sensitive.
Healing takes longer, and the risk of scarring is greater.
Full-Thickness Burns
These destroy the full thickness of the skin.
The wound may appear white, brown, leathery or charred.
The centre may be relatively painless because nerve endings are damaged.
These burns require specialist assessment and often surgical treatment.
TBSA represents the percentage of body surface affected by partial-thickness or deeper burns.
Superficial redness without blistering is not included in TBSA calculations.
For adults, the Rule of Nines provides a quick estimate:
| Body Region | Approximate TBSA |
|---|---|
| Head and neck | 9% |
| Each arm | 9% |
| Front of trunk | 18% |
| Back of trunk | 18% |
| Each leg | 18% |
| Perineum | 1% |
For smaller, scattered burns, the patient’s palm, including fingers, can be used as an approximate 1% TBSA reference.
In children, body proportions differ. The Lund–Browder chart is more accurate than the adult Rule of Nines.
Choosing a dressing requires assessment of burn depth, wound moisture, infection risk, and the need for referral.
The goal is to protect the wound, reduce pain and support healing.
Superficial burns usually do not require complex dressings.
Management may include gentle cleansing, suitable moisturising care after cooling and appropriate pain relief.
These wounds often benefit from non-adherent dressings that protect fragile skin.
Depending on the clinical situation, suitable options may include:
Dressing selection should follow the product instructions and local clinical protocols.
These require early specialist assessment because the depth may be difficult to determine and healing can be prolonged.
Doctors should avoid delaying referral while repeatedly trying different dressings.
Silver sulfadiazine remains available for selected burn-related indications.
However, it is not routinely preferred for uncomplicated superficial partial-thickness burns because it can delay healing compared with some modern dressings.
Silver-containing dressings may be appropriate in selected situations, but the choice depends on wound characteristics and specialist guidance.
A burn dressing for GP training programme should teach doctors when a basic non-adherent dressing is sufficient and when advanced wound care or referral is required.
| Burn Depth | Typical Appearance | Initial Dressing Approach | Review Timing | Refer If |
|---|---|---|---|---|
| Superficial | Red, dry, painful, no blisters | Cooling, protection and comfort measures | If symptoms worsen or healing is uncertain | Unexpected progression or concerning symptoms |
| Superficial partial-thickness | Pink, moist, painful, possible blisters | Suitable non-adherent dressing | Usually within 24–48 hours | High-risk location, larger area or uncertain depth |
| Deep partial-thickness | Pale or mottled, reduced sensation | Clean protective dressing; avoid unnecessary manipulation | Same-day specialist assessment | All suspected deep burns |
| Full-thickness | White, leathery, brown or charred | Clean, dry protective covering | Immediate specialist assessment | All full-thickness burns |
Clinical note: Review timing is illustrative. Patients with concerning symptoms, significant pain, infection signs or uncertain depth may need earlier assessment.
Knowing the burn referral criteria is one of the most important skills for a GP.
According to widely used burn referral guidance, urgent consultation or transfer should be considered for:
Children with burns may benefit from specialist consultation even when the affected area is relatively small.
Before deciding to manage a burn in primary care, confirm:
Airway and breathing are stable.
No suspected inhalation injury.
Burn depth has been assessed.
TBSA has been estimated.
No suspected full-thickness injury.
No deep burn affecting a high-risk anatomical area.
No significant blast injury or associated trauma.
Pain is adequately controlled.
Tetanus status has been reviewed.
A clear follow-up or referral plan is documented.
Important: Firecracker injuries involving the eyes require urgent ophthalmic assessment. Do not apply pressure to an eye with suspected penetrating injury.
Doctors considering burn care training in Vapi should evaluate whether the course covers practical assessment, dressing decisions and emergency referral.
An effective training curriculum should include:
Doctors should practise identifying superficial, partial-thickness and full-thickness injuries using clinical examples.
Training should include adult and paediatric burn-area estimation.
Doctors should understand non-adherent dressings, moisture balance and when specialist wound products may be appropriate.
The course should explain hand hygiene, wound cleansing, sterile technique and recognition of infection.
Participants should practise identifying patients who require immediate transfer or specialist consultation.
Doctors interested in broader surgical education can explore reconstructive surgery training and the reconstructive surgery fellowship offered through Elegance Vidhyalay.
Course participation should match the doctor’s qualifications and clinical responsibilities.
Minor burns still require appropriate follow-up.
During each visit, doctors should assess:
Dressing frequency depends on the wound and the product used.
Some modern dressings can remain in place for several days if clinically appropriate, while other dressings require more frequent changes.
Avoid unnecessary dressing removal because repeated manipulation can damage healing tissue.
Burns crossing joints may cause stiffness and contractures.
Appropriate positioning, early movement when safe, and timely rehabilitation referrals can reduce functional problems.
Once the skin has healed, selected patients may benefit from moisturising care, sun protection, silicone-based scar management or specialist scar assessment.
Deep burns and wounds that take longer to heal have a greater risk of hypertrophic scarring.
Doctors should refer patients with persistent wounds, restricted movement, or concerning scars.
For team-based wound care, the article teaching staff dressing techniques provides a structured educational approach.
Accurate wound records are equally important. Doctors can review the wound documentation protocol for documentation practices.
Burn care requires clinical judgment rather than simply applying a dressing.
Doctors must understand wound progression, tissue viability, infection risk and the indications for surgical referral.
Dr. Ashutosh Shah, MBBS, MS, MCh, DNB, is a Plastic and Reconstructive Surgeon with more than 22 years of clinical experience and is associated with Elegance Vidhyalay. His surgical background highlights the importance of systematic wound assessment, safe dressing practices, early recognition of deep burns and timely specialist referral.
A structured burn management course for doctors should combine theoretical knowledge with supervised clinical demonstrations, case discussions and practical assessment.
Yes, silver sulfadiazine may still be used in selected cases. However, it is not routinely the first choice for uncomplicated superficial partial-thickness burns because some modern dressings support faster healing. Treatment should depend on burn depth, infection risk and clinical guidance.
Children have different body proportions from adults. The Lund–Browder chart adjusts TBSA estimates according to age and is preferred for paediatric burn assessment. A doctor considering burn care training in vapi should ensure the curriculum includes paediatric TBSA calculations.
Blister management depends on size, location, function and clinical circumstances. Small intact blisters may be left undisturbed, while large, ruptured or function-limiting blisters may require assessment and selective debridement by an appropriately trained clinician. Routine deroofing of every blister is not recommended.
Tetanus vaccination status should be assessed for every burn patient. Burns can be considered tetanus-prone wounds. A booster and, in selected cases, tetanus immune globulin may be required according to immunisation history and applicable guidelines.
Skin grafting may be required for full-thickness burns and selected deep partial-thickness burns that are unlikely to heal promptly. The decision depends on burn depth, location, tissue viability and specialist assessment.
The interval depends on wound condition and dressing type. Some dressings require daily changes, while others may remain in place for several days. Increasing pain, leakage, odour, fever or signs of infection require earlier clinical review.
Diwali-related burn injuries can range from minor superficial wounds to serious burns requiring emergency surgery.
GPs and casualty doctors play an important role in early assessment, cooling, dressing selection and referral.
A burn management course for doctors should strengthen practical skills in burn-depth assessment, TBSA estimation, wound care, tetanus evaluation and recognising complications.
Doctors should remember the essential principles: provide 20 minutes of cool running water, avoid harmful home remedies, assess the full injury and refer deep or high-risk burns promptly.
Elegance Vidhyalay provides educational pathways related to reconstructive surgery and clinical skill development. Doctors should evaluate course eligibility, faculty supervision and practical exposure before enrolling.



